


Quick answer: In the intraoral scanner vs AI dental screening decision, the two devices do different jobs. An intraoral scanner creates a 3D digital impression for crowns, bridges, aligners and implant work, so it earns its keep on treatment the clinic already does. An AI dental screening device captures standardized 2D photos and flags visible signs such as possible cavities, tartar and gum inflammation, so it earns its keep by starting more patient conversations. If your bottleneck is impressions, buy a scanner. If your bottleneck is getting people into the chair, look at screening. Many growing clinics end up with both.
The "intraoral scanner vs AI dental screening" question comes up because both devices sit in the "digital dentistry" budget line and both involve cameras. That is where the similarity ends. This guide compares them fairly, as of September 2026, so you can decide based on your clinic's workflow rather than a sales pitch.
scanO makes an AI dental screening device (scanO air). We are not affiliated with any intraoral scanner brand. Buyers should confirm specifications and prices with authorized dealers.
An intraoral scanner is a handheld wand connected to a computer. It projects light onto the teeth and soft tissues, captures many images and stitches them into a 3D model. That model replaces a conventional alginate or silicone impression.
A widely cited review in BMC Oral Health describes intraoral scanners as tools for capturing digital impressions used in restorative dentistry, implant prosthetics and orthodontics. It lists benefits such as reduced patient discomfort, time efficiency and easier communication with labs, and drawbacks such as a learning curve, purchase and management costs, and difficulty capturing deep margins (Mangano et al., BMC Oral Health, 2017).
In short, a scanner improves the quality and speed of treatment you are already delivering. It does not, by itself, create new patients.
AI dental screening captures a small set of standardized intraoral photos and runs computer vision software that flags visible findings. The result is a color-coded report that a patient can understand and a dentist can review.
It is a triage and communication tool. It helps a clinic identify who may need a full examination, and it gives patients a visual reason to book one. It does not diagnose, and it does not replace radiographs or a clinical examination. We explain the full process in our guide on how AI dental screening works.
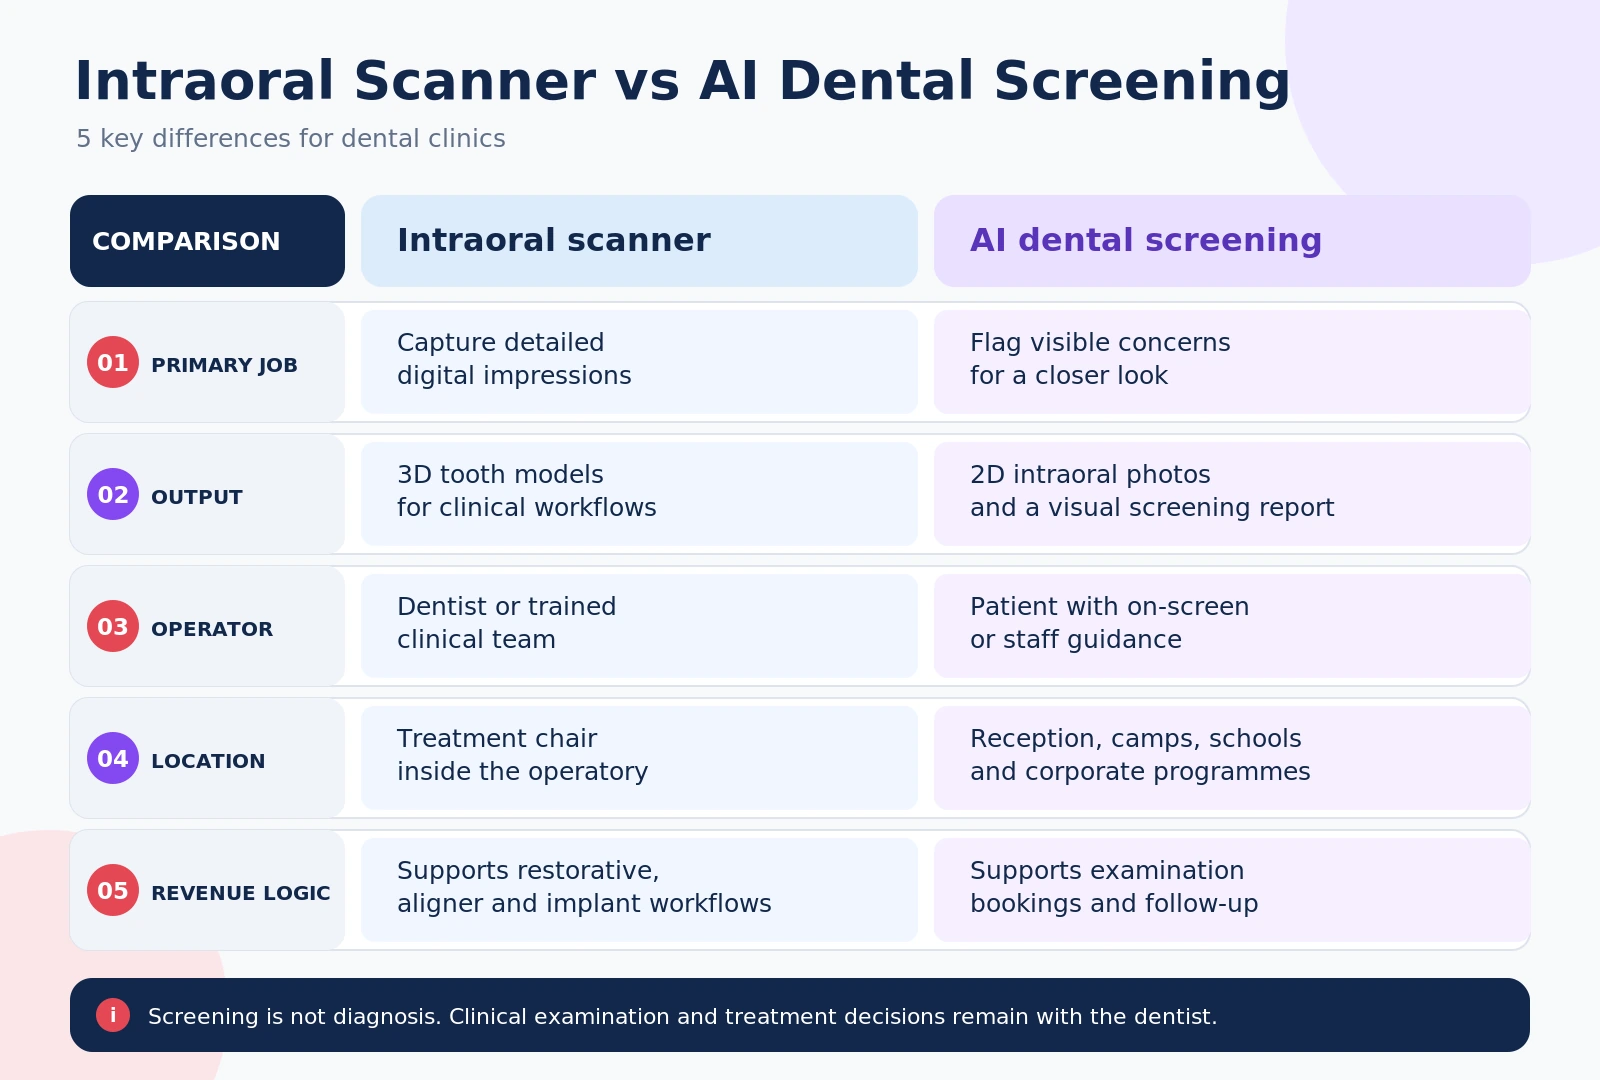
This table compares the two categories, not specific brands. Individual products vary, so check each point with the vendor.
The honest takeaway: the two devices do not compete on the same job. Comparing them on "accuracy" misses the point, because they are not measuring the same thing.
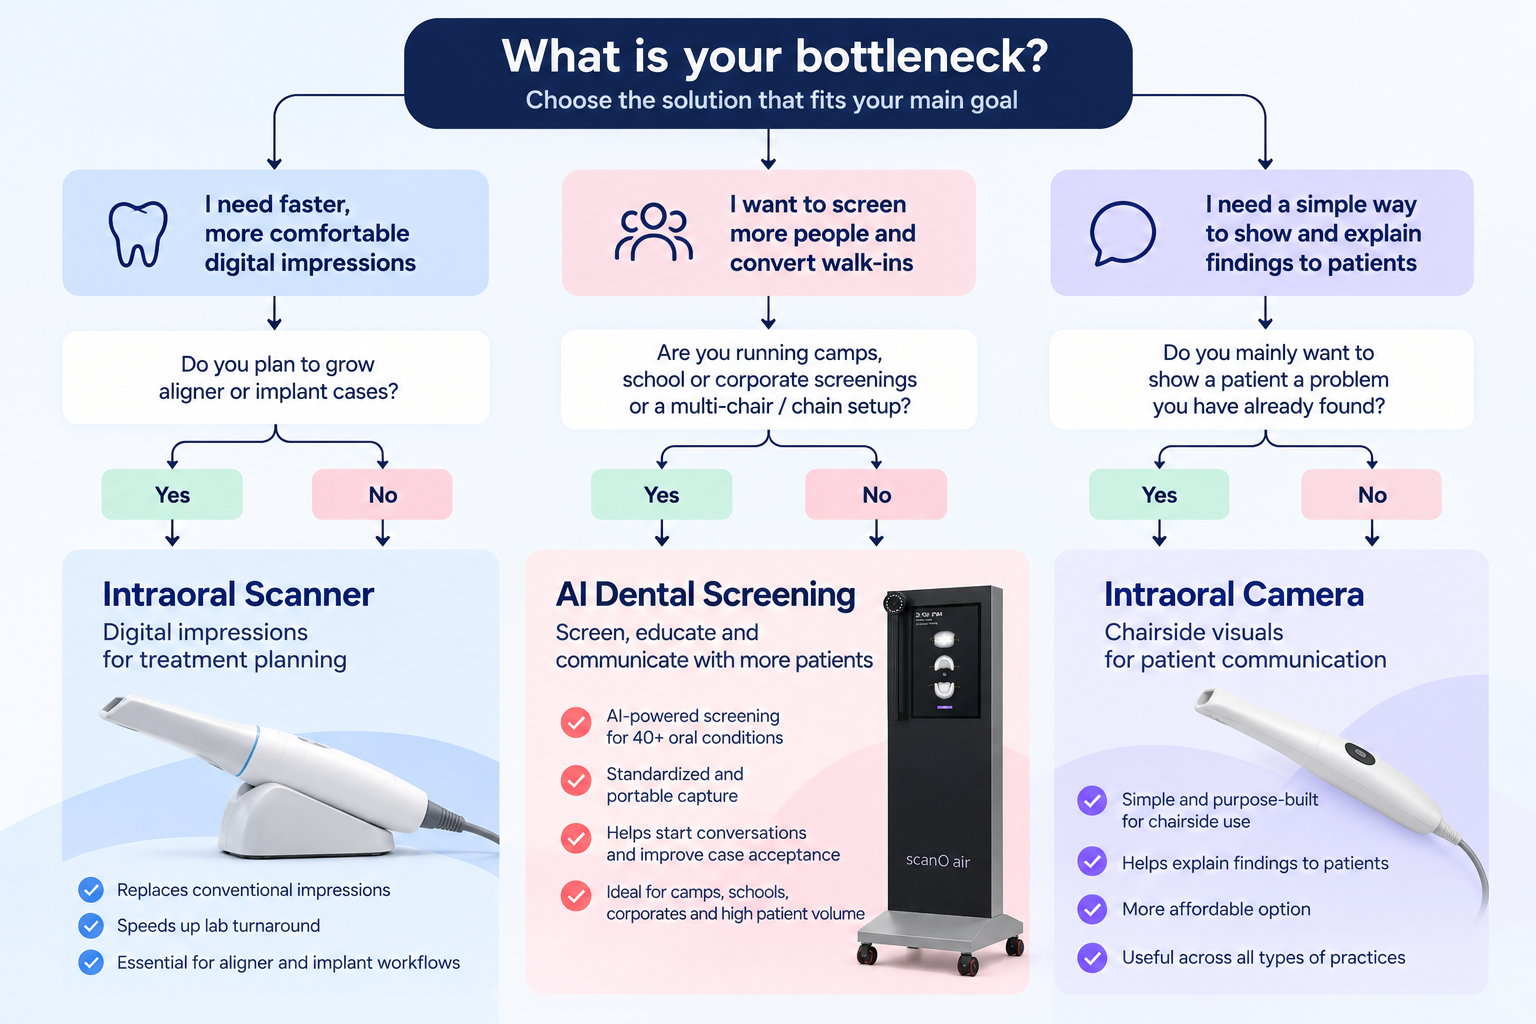
Use your clinic's main bottleneck to decide.
People searching "intraoral scanner vs intraoral camera" are often really asking about patient communication. An intraoral camera is a handheld device the dentist uses chairside to show live images on a screen. It does not build a 3D model, and it usually does not run automated analysis.
Think of it this way: the camera shows the patient what the dentist already sees, the scanner builds a model for treatment, and AI screening flags who may need a closer look before they reach the chair. Our intraoral camera buying guide covers prices and features in detail.
Because the devices do different jobs, compare them on what each one changes in your clinic, not on sticker price alone. Fill in this worksheet with your own numbers.
For the screening column, the key number is how many screened people book an examination and go on to accept treatment. Track it for three months before judging. The ROI calculator can help frame the estimate.
Example scenario (hypothetical, for illustration only). A three-chair clinic in a metro suburb does a moderate number of crowns and has started offering aligners. Its chairs are busy on weekday evenings but quiet in the mornings, and front-desk staff notice that relatives who accompany patients rarely book for themselves.
The owner lists two problems: impressions are slow and uncomfortable for aligner cases, and new-patient flow is flat. A scanner addresses the first, screening addresses the second. With budget for one device this year, the owner compares the worksheet figures. Because aligner growth depends on digital impressions, the scanner goes first, with screening planned for the next financial year alongside a school outreach program.
A different clinic with low prosthodontic volume but high footfall would reasonably make the opposite call.

The right choice depends on the bottleneck in your workflow, not on which device sounds more advanced. scanO air belongs to the visual oral screening category. It uses intraoral images to support screening and visual patient communication. It does not create impressions, and it is not a substitute for an intraoral scanner, radiographs, a clinical examination, diagnosis or treatment planning. The dentist makes every clinical decision.
An intraoral scanner creates a 3D digital impression for treatment such as crowns, aligners and implants. AI dental screening captures 2D photos and flags visible signs that may need a dentist's attention. One supports treatment, the other supports triage and patient communication.
No. AI screening devices do not produce 3D models, so they cannot be used for digital impressions, lab work or aligner planning.
A scanner captures detailed images, and some scanner software offers additional analysis features, but it is operated chairside by trained staff and is not designed for quick, high-volume screening at reception or camps. Check the specific features with the manufacturer.
An intraoral camera shows live and still images of the mouth for patient communication. An intraoral scanner stitches many images into a 3D model for digital impressions. Cameras cost far less and do not replace impressions.
It depends on the bottleneck. Clinics with steady crown, aligner or implant work usually benefit from a scanner first. Clinics that need more new-patient conversations, or plan camps and school programs, often get more value from screening first.
Yes. Take informed consent before capturing photos, take parental consent for children, and handle the data in line with India's Digital Personal Data Protection Act, 2023.
For a broader view of use cases, evidence and adoption, read our guide to AI in dentistry.
Decide with the device in front of you. If screening is the gap in your patient journey, book a personalized scanO air walkthrough and see how it would sit alongside the scanner and camera you already use or plan to buy.




